When several teeth, gums, the bite and jaw function are failing together, treating one tooth at a time can leave the underlying problems unresolved. By the end, you will know which examinations come first, how treatments are staged, and how dentists decide between preserving a natural tooth and replacing it.
Key takeaways
- Full mouth rehabilitation coordinates several treatments around health, function and appearance.
- Expect photographs, X-rays, bite records and a tooth-by-tooth treatment plan.
- Ask which teeth can be preserved before considering extraction, implants or major restorations.
- Confirm treatment stages, alternatives, risks, maintenance needs and total appointments.
What does full mouth rehabilitation mean, and who needs it?
Full mouth rehabilitation is a coordinated plan for several connected dental problems, not one procedure. Also called full-mouth reconstruction, it may combine restorative, periodontal, endodontic, orthodontic, surgical, implant and prosthodontic care. The aim is to restore health, chewing, comfort and appearance while protecting the teeth and supporting tissues.
You may fit this approach if you have:
- Multiple failing teeth
- Extensive decay requiring an extensive decay treatment plan
- Advanced tooth wear from erosion, grinding or other causes
- Several missing teeth or widespread tooth loss
- A bite problem affecting function or tooth survival
- Gum disease alongside damaged or missing teeth
- A combination of these conditions
Full mouth rehabilitation does not mean placing crowns on every tooth. Each tooth receives only treatment justified by its condition, remaining structure and prognosis. That treatment could be preventive care, a filling, an onlay, root canal treatment, orthodontic movement, extraction or no treatment.
| Option | What it means | When it applies |
|---|---|---|
| Single filling | Repairs one limited cavity or defect | One tooth needs treatment |
| Routine restorative care | Treats separate fillings, crowns or similar needs | Problems are limited and not strongly connected |
| Cosmetic smile makeover | Primarily changes visible tooth appearance | Appearance is the main concern |
| Full arch implant treatment | Replaces most or all teeth in one arch with implants and a prosthesis | An arch has widespread tooth loss or hopeless teeth |
| Full mouth rehabilitation | Coordinates treatment across the mouth | Multiple teeth, gums, bite or function require one integrated plan |
What happens during the first consultation and diagnostic work-up?
Diagnosis comes before treatment selection. An initial dental consultation starts with your medical and dental history, including conditions, medicines, allergies, previous treatment, smoking, clenching, jaw-joint symptoms and chewing-muscle discomfort.
1. The dentist examines every tooth individually, checking decay, cracks or fractures, existing fillings and crowns, tooth mobility, gum condition and tooth wear. Periodontal charting records pocket depths and bleeding points around each tooth, while a tooth-by-tooth prognosis identifies teeth that are restorable, questionable or unlikely to last.
2. The records show how your teeth meet and function. They may include dental photographs, bite records, facial-proportion measurements, digital scans or conventional impressions, plus notes about speech, chewing and jaw movement.
3. X-rays answer different questions. Bitewing radiographs help detect decay between teeth and assess bone levels; periapical images show individual roots, surrounding bone and possible infection; a panoramic image provides a broad view of both jaws, missing teeth and developing problems.
CBCT is reserved for questions that two-dimensional X-rays cannot answer. Examples include measuring implant bone volume, locating an important nerve or evaluating complex root anatomy; it is not an automatic part of every consultation.
Before recommending treatment, the dentist should document tooth wear, facial proportions, jaw-joint and chewing-muscle symptoms, clenching risk and the prognosis of every questionable tooth. That evidence supports a staged plan instead of choosing crowns, implants or extractions from appearance alone.
How are the procedures sequenced across a full mouth plan?
The sequence is staged dental treatment, not a fixed recipe or a single appointment. The order changes with infection, gum health, tooth prognosis, bite, healing needs and the patient’s ability to keep the mouth clean.
1. Risk reduction comes first. Urgent pain, infection, active decay, gum disease and plaque-control problems receive attention before definitive crowns, bridges or implant restorations. This is disease control before restorations; otherwise bacteria, inflammation or poor hygiene can damage restoration margins and supporting tissues.
2. The dentist then completes the treatments each tooth requires. These may include fillings, root canal treatment, periodontal therapy, extractions, orthodontic movement or implant surgery. Not every tooth needs a crown, and surgery is delayed when a tooth can be saved predictably.
3. Provisional restorations may replace missing teeth or cover prepared teeth while the plan is tested. They reveal whether tooth shape, speech, chewing comfort, cleansability and the proposed bite work in daily life.
4. Surgical sites and implants need recovery before final work proceeds. Implant healing time and integration into bone can extend the schedule, while gum treatment may require reassessment before restoration.
5. Definitive crowns, bridges, implant restorations or dentures are made after the tissues are stable and the provisional design works. Follow-up then checks the bite, hygiene and maintenance needs.
A flare-up, poor plaque control or an adjustment to the temporary teeth can change later appointments. Delaying final restorations protects the result rather than signalling that treatment has failed.
How does the plan account for bite, tooth wear and natural-tooth preservation?
The plan begins with a bite assessment: how the upper and lower teeth meet, where the jaw sits, how much restorative space exists, and how chewing forces are distributed. Dentists also assess tooth wear, facial proportions and speech before designing restorations.
1. Vertical dimension of occlusion is a clinical decision, not an automatic part of rehabilitation. Changing the jaw-to-jaw tooth relationship may help when wear, limited space or function requires it, but reducing healthy teeth only to create a new bite can cause unnecessary, irreversible damage.
Temporary restorations can test comfort, speech and chewing before that decision becomes permanent.
2. Each tooth receives treatment according to its structure and prognosis, not because the plan is called full-mouth rehabilitation. Orthodontics can move tilted, crowded or over-erupted teeth into a better position, creating restorative space and reducing the amount of tooth preparation.
3. Compare preserving a treatable natural tooth with removing it. The choice depends on remaining tooth structure, periodontal support, infection, mobility and expected longevity.
| Option | Surgery and timing | Maintenance and prognosis |
|---|---|---|
| Natural tooth with filling or root canal | Usually avoids extraction; appointments depend on decay or infection | Preserves existing support; prognosis depends on the remaining structure and gum health |
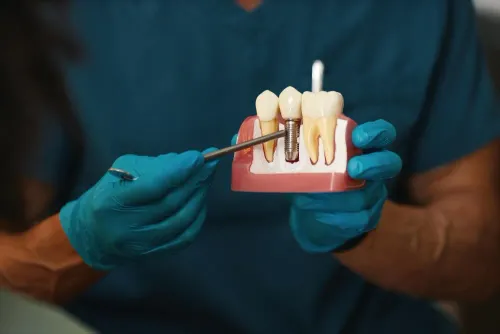
| Extraction with implant | Requires surgery, healing and often several appointments before the final crown | Needs cleaning and professional review; prognosis depends on bone, gums and loading |
| Extraction with bridge or denture | Requires preparation or impressions, with no implant integration period | Requires replacement or adjustment as supporting teeth and tissues change |
Bruxism or clenching can alter material choice, restoration thickness and bite design. A night guard or other protective appliance may be needed to reduce fracture and wear.
What should you confirm before accepting a full mouth rehabilitation plan?
Do not accept a plan based only on a more attractive smile or a high procedure count. Ask for a written, tooth-by-tooth prognosis and treatment sequence before signing dental treatment consent.
- Which teeth are restorable, questionable or hopeless, and why is each procedure recommended?
- Which stages are reversible, and which involve permanent tooth reduction, extraction or surgery?
- What temporary teeth will you wear, and will they test speech, chewing, cleansability and the proposed bite?
- How long will healing, implant integration and adjustment appointments take?
- What happens if an implant, crown or bridge loosens, chips, fractures or fails?
| Confirm | Why it matters |
|---|---|
| Bite and materials | The proposed bite and material choice must match tooth wear, chewing forces and bruxism risk. |
| Home care and protection | Get written hygiene instructions, peri-implantitis prevention advice and a bruxism guard plan. |
| Maintenance and recalls | Confirm dental restoration maintenance tasks and the recall schedule before treatment begins. |
| Failure arrangements | Ask who manages repairs, replacement, added surgery and costs if treatment fails. |
Full mouth rehabilitation is a long-term maintenance commitment, not a permanent cure. Natural teeth can develop recurrent decay; restorations can chip or loosen; implants can develop peri-implant mucositis or peri-implantitis.
Kaira Dental Care & Implant Centre in Thane can be used to review records and full mouth treatment plan questions, but the useful outcome is a documented plan with alternatives, risks, healing times and maintenance duties—not a decision made from appearance alone.
Related services
Full Mouth Rehabilitation Dr. Ashi Agarwal, an experienced Dental Surgeon at her clinic on Wagbil Road, Kavesar, Thane West, offers comprehensive Full Mouth Rehabilitation... View service → |
Full Arch Implants Dr. Ashi Agarwal, a dedicated Dental Surgeon at her clinic on Wagbil Road, Kavesar, Thane West, offers advanced Full Arch Implant solutions for... View service → |
Frequently asked questions
What does full mouth rehabilitation mean, and who needs it?
Full mouth rehabilitation is a coordinated plan for multiple connected problems, such as severe tooth wear, decay, gum disease, missing teeth, bite problems or failing dental work. It may combine restorative, periodontal, endodontic, orthodontic, surgical, implant and prosthodontic treatment.
What happens during the first consultation and diagnostic work-up?
The assessment can include a medical and dental history, clinical examination, photographs, dental X-rays, periodontal measurements, tooth-by-tooth findings, bite records and evaluation of tooth wear. The dentist uses these records to identify disease, assess which teeth are restorable and build treatment options.
How are the procedures sequenced across a full mouth plan?
Treatment usually begins with urgent problems and disease control, including pain relief, infection treatment, gum therapy and oral-hygiene measures. The plan then addresses tooth preservation, bite or alignment, missing teeth and definitive restorations, with healing and review between stages.
How does the plan account for bite, tooth wear and natural-tooth preservation?
The plan records how the upper and lower teeth meet, evaluates wear patterns and identifies forces that could damage new restorations. It should explain which natural teeth can be repaired, when a root canal or crown is appropriate, and when extraction is unavoidable.
What should you confirm before accepting a full mouth rehabilitation plan?
Ask for the diagnosis, treatment sequence, alternatives, expected lifespan of restorations, risks, maintenance requirements, number of appointments, healing periods and itemised fees. Confirm who will provide each stage and how the bite will be checked before final restorations are fitted.